Mechanisms, Use Cases & High-Yield Step 2 CK Exceptions Explained
🧪 1. Medication Classes Overview

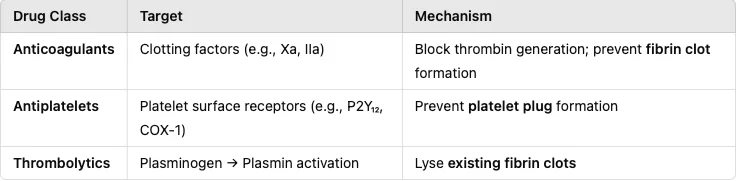
⚙️ 2. Mechanism of Action Comparison
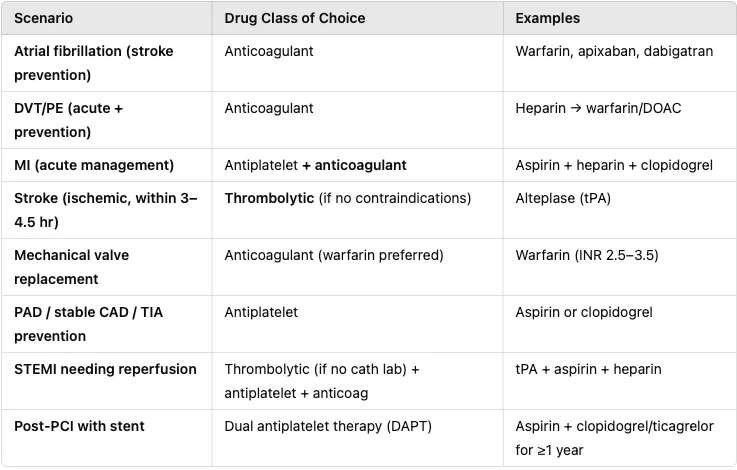
📚 3. Clinical Use Cases
📌 4. Key Step 2/CK + NBME Tips
Anticoagulants = prevent new clots (do not break existing ones).
Thrombolytics = used acutely to dissolve thrombi (e.g., ischemic stroke, STEMI without PCI).
Antiplatelets = arterial clots (e.g., coronary, cerebral) — platelets matter more in high-flow systems.
Anticoagulants = venous clots (DVT/PE) — coagulation cascade driven.
Never combine anticoagulants + antiplatelets long term unless absolutely indicated (↑↑ bleeding risk).
Thrombolytics are contraindicated in most cases of recent surgery, active bleeding, or hemorrhagic stroke history.
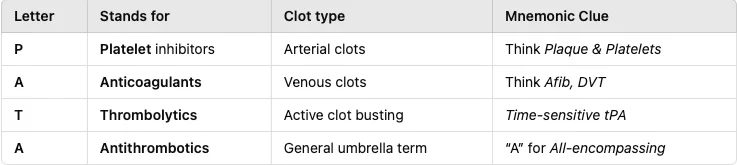
🧠 Mnemonic: "PAT-A"
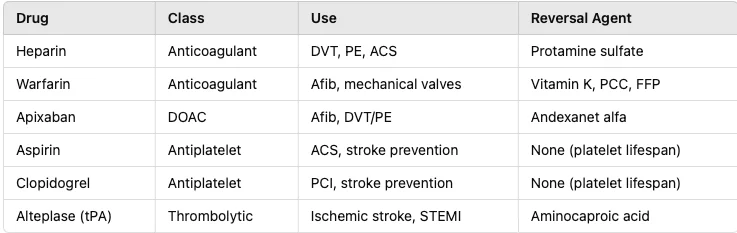
💊 Drug Quick Sheet
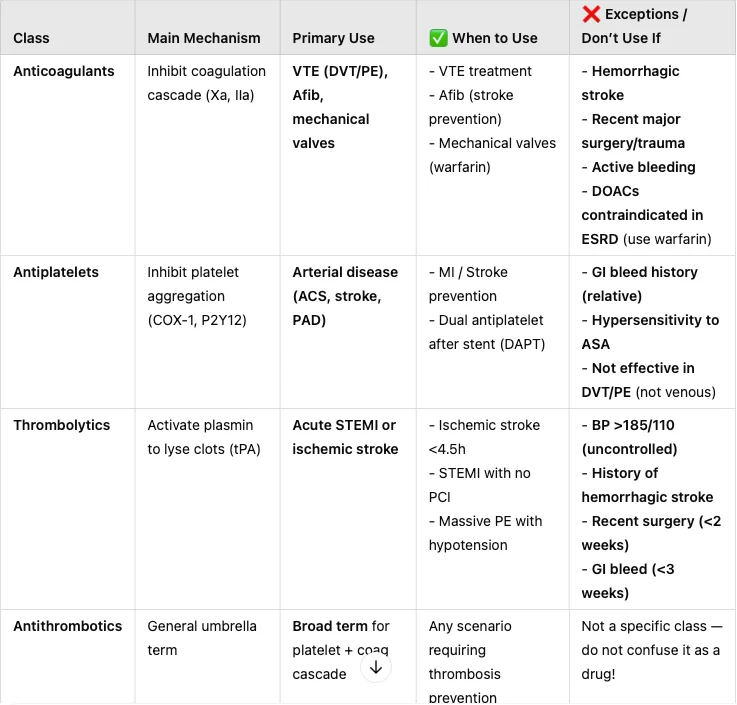
🧠 Master Table with EXCEPTIONS and Nuance
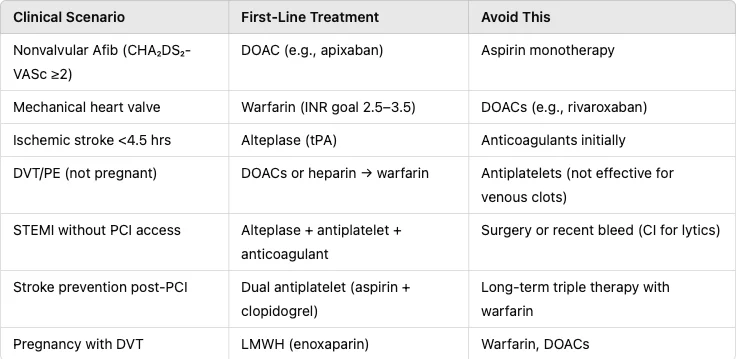
🧩 NBME/Step-Style Exceptions
🧬 1. Atrial Fibrillation
✅ Use anticoagulants to prevent embolic stroke.
❌ Don’t use aspirin alone unless patient is at low CHA₂DS₂-VASc score (e.g., score = 0).
⚠️ Mechanical heart valve → must use warfarin (NOT DOACs like apixaban).
🩸 2. Post-MI
✅ Dual antiplatelet therapy (DAPT) (aspirin + clopidogrel/ticagrelor) after PCI.
❌ Avoid triple therapy (anticoagulant + 2 antiplatelets) unless compelling indication — increased bleeding risk.
⚠️ If patient is on warfarin for Afib + just got a stent, limit DAPT duration and monitor closely.
🧠 3. Ischemic Stroke
✅ Thrombolytics (tPA) if <4.5 hours, and patient meets criteria.
❌ Do NOT give tPA if:
BP >185/110
INR >1.7
Platelets <100k
Glucose <50 or >400
Stroke >1/3 of MCA territory on CT
🦵 4. DVT/PE
✅ Start with heparin, then bridge to warfarin or start DOAC directly.
❌ Avoid DOACs in severe renal failure (CrCl <30 mL/min) → use warfarin instead.
👶 5. Pregnancy
✅ Use LMWH (enoxaparin) or UFH (doesn’t cross placenta).
❌ Avoid warfarin → teratogenic, esp. in 1st trimester.
❌ Avoid DOACs → insufficient safety data in pregnancy.
💥 6. Massive PE with Hypotension
✅ Use thrombolytics (alteplase) if:
Patient is unstable (shock, hypotension)
❌ Do not delay lytics for CT angiogram if clinical signs of massive PE and patient crashing.
🛡️ Summary Chart: What's First-Line vs When to Avoid
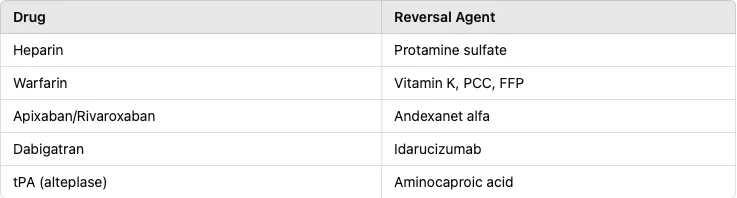
⚠️ Bonus: Reversal Agents (Must-Know for Emergencies)